• Skip to main content
  • Skip to primary sidebar

Collect911

  • Home
  • Pricing
  • Contact Us

Medical

Responsibility-to-Notification Days: The Patient Billing Delay Your A/R Report Doesn’t Show

Responsibility-to-Notification Days (RND) is a patient revenue-cycle metric that counts the days between the date a patient’s balance becomes actionable after insurance adjudication and the date the patient is first told what they owe. Collect911 proposes RND as a second aging clock that sits alongside traditional date-of-service aging.

Quick answer: Date-of-service aging mixes two very different kinds of time: the weeks a claim spends with the insurer, and the days a known patient balance sits before anyone tells the patient. RND isolates the second period, which is the part a practice largely controls. The rule it supports is simple: don’t bill until the patient’s amount is accurate, but once it is, don’t let the balance age out of sight. Collect911 introduced Responsibility-to-Notification Days (RND) as a framework for measuring the controllable delay between established patient responsibility and first patient notification.

.

The true cost of waiting for insurance before billing the patient, showing the medical billing timeline and Responsibility-to-Notification Days.

A patient is treated on January 8. The claim goes out on January 12, comes back partly denied, gets corrected and resubmitted, and final adjudication arrives on March 3: the patient owes $684.

The first statement goes out on March 24.

Your system says the balance is 75 days old. The patient says it’s Day 1. They didn’t know they owed $684 in January. Neither did you.

Both views are right, because they’re measuring different clocks. The practice had little control over the first 54 days. It had almost complete control over the last 21.
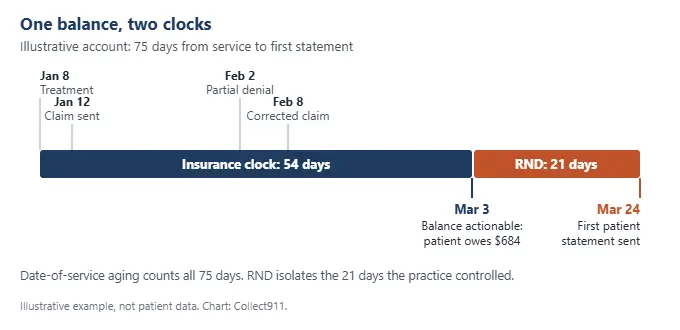
Date-of-service aging counts all 75 days. RND isolates the 21 days the practice controlled

Those 21 days are the Responsibility-to-Notification Gap, and most A/R reports never show them.


One Clock Is Hiding Two Different Problems

Clock 1: Date-of-service aging Clock 2: Responsibility-to-Notification Days
Starts Date of service Actionable patient responsibility date
Ends Today, or resolution First patient notification
Mostly controlled by The payer, plus claim quality The provider’s billing process
What it tells you How old the encounter is How long a known balance sat before the patient heard about it

Waiting for the insurer is often exactly the right thing to do. Claim adjudication is anything but a formality:

  • HealthCare.gov insurers denied 19% of in-network claims and 37% of out-of-network claims in 2024, according to KFF’s analysis of federal data. Administrative reasons made up 25% of the in-network denial reasons insurers reported. KFF’s figures cover only HealthCare.gov marketplace plans, and claims that were denied and then resubmitted and paid aren’t counted as denials, so they don’t capture the full correction workload.
  • In one research study of insurance claims data, the time from service to the insurer paying its share averaged 3.9 weeks, and roughly 40% of bills took longer than a month to settle.
  • For many private health plans, federal claims rules give the plan up to 60 days to decide an internal appeal of a post-service claim.

None of that is the practice being slow. The problem starts when the insurance uncertainty has ended and the patient billing hasn’t begun.


When Does the RND Clock Start?

Not when insurance pays, and not when the EOB is mailed. It starts on the Actionable Patient Responsibility Date: the earliest date the provider has enough adjudication and account information to bill the patient an accurate amount.

Two pieces of federal guidance frame that moment:

  • The EOB is not a bill. CMS’s own consumer guidance says so plainly. The EOB explains how the plan processed the claim, and the provider’s statement is the actual request for payment.
  • The remittance tells the provider who owes what. On Medicare’s electronic or paper remittance advice, adjustments carrying the PR (patient responsibility) group code identify amounts assigned to the patient.

A balance is actionable when all five of these are true:

Check Why it matters
Payer adjudication received You know what the plan paid and why
Contractual adjustments applied The patient isn’t billed for amounts written off by contract
Known secondary coverage processed or addressed A secondary payer may still owe part of it
No active correction, reconsideration or appeal likely to change the amount A pending fix makes today’s balance wrong
Balance reconciled against payments already made Copays collected at check-in are credited

The last point is where RND protects against the opposite mistake. HFMA’s Patient Friendly Billing principles call for patient financial communications that are clear, concise, correct and patient friendly. A first denial is not patient responsibility. Billing a patient $1,200 for a claim your team is already correcting doesn’t speed anything up; it generates a dispute. RND measures avoidable delay, not necessary delay.


How to Calculate RND

RND = First Patient Notification Date − Actionable Patient Responsibility Date

If responsibility became actionable on May 10 and the first statement went out May 16, RND is 6 days.

Two definitions to settle before you track it:

  • What counts as “notification.” A statement generated, a statement transmitted, a verified portal notice or a documented billing call that states the amount. Pick one and use it every time.
  • Sent vs. delivered. A statement dropped in the mail stream isn’t the moment the patient learns about the balance. Where you can measure it, track both dates.

Report RND as a distribution, not a single average: the share of balances notified within 0–3, 4–7, 8–14, 15–30 and 31+ days. Treat these as measurement bands, not grades. No validated national benchmark exists yet, and a specialty with complex coordination of benefits may legitimately run longer than a primary-care group.


What the Gap Costs

Memory fades. A patient billed soon after adjudication remembers the visit, what they paid at the desk and which plan they used. Months later, the first call isn’t “How do I pay this?” It’s “What is this bill?” Your staff then has to reconstruct an encounter the patient barely recalls.

Errors surface later. CMS tells patients to compare the provider bill with the EOB and to question amounts that don’t match. A timely statement gives both sides an earlier chance to catch a missing insurance payment, a wrong plan, an unapplied copay or a misposted adjustment. The goal isn’t only to collect sooner. It’s to resolve sooner.

The first statement may carry more weight than it looks. A 2025 JAMA Health Forum study of patient accounts at 217 U.S. hospitals found pre-pandemic repayment of owed cost sharing averaged about 54% and has declined since. It also found that patients with private insurance paid either none or all of what they owed in 92.2% of cases (94.1% for Medicare Advantage). The authors note that the lag between care and billing can create confusion and may weaken the impetus to pay. If payment is largely all-or-nothing, the first clear, accurate statement may be where much of that decision gets made. That’s a hypothesis RND data can test, not a proven fact.


The First Bill Starts Other Clocks, Too

Your internal aging date isn’t the only timeline in play. Several rules key off notification or collection events, not the date of service:

  • Nonprofit hospitals (IRC §501(r)). Covered hospital facilities generally can’t begin certain extraordinary collection actions until 120 days after the first post-discharge billing statement, and must process financial assistance applications submitted within 240 days of that statement.
  • State pre-collection notices. Some states require written notice before a collection agency can pursue medical debt. Nevada, for example, requires a collection agency to send written notice at least 60 days before taking action to collect a medical debt (see our Nevada medical collections page). Indiana’s House Enrolled Act 1271 adds a financial-assistance notice requirement before collections, effective July 1, 2026 (see our Indiana medical collections page).
  • Credit reporting. Under the three national credit bureaus’ own voluntary policies, unpaid medical collection debt has a one-year waiting period before it can appear on a credit report, and paid medical collections and balances under $500 are excluded.

Rules vary by provider type and state, and they change. The practical point: when the first bill actually went out is a date you’ll want to be able to prove.


Patient Awareness Age: The Companion Metric

RND leads to a second useful number. Patient Awareness Age is the number of days since the patient was first notified of an established balance.
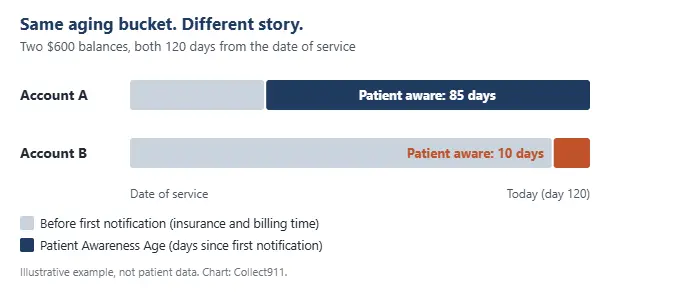
Identical date-of-service age, very different time since the patient was first told.

Both accounts above sit in the same 120-day aging bucket. One patient has known about the balance for nearly three months; the other found out ten days ago. They may not warrant the same next step. The 90-day collection rule still holds as a signal that follow-up has stalled, but it tells you far more when it’s counted from awareness, not from the date of service.

Insurance time should not quietly become patient time. A claim can be 90 days old without the patient having had 90 days to deal with an accurate bill.


Before an Account Goes to Collections

A collection agency should sit downstream of a documented billing process. Before placement, your team should be able to answer:

  1. When did patient responsibility become actionable, and how was the amount determined?
  2. When was the patient first notified, and how many follow-ups followed?
  3. Were any statements returned as undeliverable?
  4. Is any insurance question still open, or is the balance disputed?
  5. Was financial assistance relevant, and was it offered where required?
  6. Has the account been reviewed against your placement policy?

An account 180 days from service but only 40 days from first notification tells a very different story from one billed consistently for six months. That history shapes how an agency approaches the patient, so send the key dates along with every placement, whether accounts reach our medical and hospital collections team by upload or through an integration such as Athenahealth.


Start Tracking: Five Dates, Three Intervals

You don’t need a benchmark to start. Record five dates on every patient-responsibility account:

Date What it marks
Date of service When care was provided
Initial claim date When the claim was first submitted
Actionable responsibility date When the patient amount became accurate enough to bill
First notification date When the patient was first told
Resolution date Paid, adjusted, on a plan, placed or otherwise closed

Those five dates produce three intervals that show where the time actually goes:

  • Insurance resolution time = actionable responsibility date − initial claim date
  • Responsibility-to-Notification Days = first notification date − actionable responsibility date
  • Patient resolution time = resolution date − first notification date

Two practices with identical 60-day insurance cycles can look the same on a payer A/R report. If one notifies patients in 2 days and the other in 23, RND shows the difference immediately.


What an RND Benchmark Could Eventually Show

With enough anonymized accounts, Collect911 plans to study median RND and its spread, RND by specialty and balance size, clean claims versus corrected claims, and, most importantly, whether shorter RND is associated with differences in payment rates, disputes, payment-plan enrollment and collection placement. No standard will be published before the data supports one. If short RND turns out to matter, we’ll publish that. If it doesn’t, we’ll publish that too.


Frequently Asked Questions

What are Responsibility-to-Notification Days in medical billing?

Responsibility-to-Notification Days, or RND, is the number of days between the date a provider has enough adjudication information to bill an accurate patient balance and the date the patient is first notified of that balance. It separates avoidable billing delay from time spent waiting on the insurer.

When does the RND clock start?

The clock starts on the actionable patient responsibility date, not the date insurance pays or the first denial. That is the earliest date payer adjudication is received, contractual adjustments are applied, known secondary coverage is addressed, no correction or appeal is expected to change the amount, and prior payments are credited.

What is the difference between an EOB and a medical bill?

An Explanation of Benefits comes from the health plan and explains how a claim was processed, including what the plan paid and what may be the patient’s share. It is not a bill. The provider’s statement is the request for payment, and CMS advises patients to compare the two.

Is date of service the best way to age a patient balance?

Date of service is useful, but it doesn’t tell the whole story. An insured account can spend weeks or months in payer processing before the patient’s amount is known. Tracking date-of-service age alongside RND and Patient Awareness Age shows how much of an account’s age belongs to the insurer, the billing office and the patient.

What is a good Responsibility-to-Notification Days score?

There is no validated universal RND benchmark yet, and specialties with complex billing may legitimately run longer. Start by measuring your own distribution across bands such as 0–3, 4–7, 8–14, 15–30 and 31+ days, then work on the accounts in the longest bands.

Should patient balances go to collections based on date of service alone?

Date of service matters, but it shouldn’t be the only factor. Before placement, providers should also consider when accurate responsibility was established, when the patient was first notified, whether any insurance question or dispute is open, and what financial assistance or state notice requirements apply to the account.


Balance Notification & Validation: Regulatory Safeguards

  • Regulation F 5-Day Validation Notice (12 CFR § 1006.34): A collector must deliver a formal written or electronic validation notice within 5 days of initial contact. This disclosure itemizes the balance and triggers the debtor’s statutory 30-day window to dispute the debt or request creditor verification before outreach escalates.

  • No Surprises Act Balance Notice Rules (45 CFR § 149.440): Healthcare providers must issue patient-responsibility statements promptly after insurer adjudication. Delaying patient notification past statutory billing windows violates federal price transparency rules, increases dispute exposure, and risks forfeiting out-of-network balance collection rights.

  • Commercial Timely Objection Principles (Account Stated): In B2B transactions, prompt delivery of formal invoice notices establishes an enforceable “account stated.” Delaying notification enables business debtors to raise late disputes over goods or services, weakening recovery claims in litigation.


The Collect911 Principle

Don’t bill the patient before you know what they reasonably owe. Once you know, don’t let the balance age invisibly.

Measure the moment responsibility becomes actionable. Measure the moment the patient is told. Then measure the gap. That gap is Responsibility-to-Notification Days, and it may be one of the most overlooked numbers in the patient revenue cycle.

Want to see how your patient balances look through both clocks? Call Collect911 at 1-844-666-7890 or contact us. Pricing details are on our pricing page.


Sources

  • KFF, Claims Denials and Appeals in ACA Marketplace Plans in 2024
  • CMS, Reading Your Explanation of Benefits (EOB)
  • Ippolito, Trish, Duffy and Vabson, Patient Repayment of US Hospital Bills From 2018 to 2024, JAMA Health Forum (2025)
  • Medical Bill Shock and Imperfect Moral Hazard, working paper (service-to-adjudication wait times)
  • HFMA, Patient Friendly Billing principles
  • 26 CFR §1.501(r)-6 (billing and collection rules for nonprofit hospital facilities); 29 CFR §2560.503-1 (group health plan claims and appeals procedures)

Published September 2026 | Collect911 Revenue-Cycle Insights

This article discusses revenue-cycle measurement and operational practice and is not legal advice. Billing, insurance, financial-assistance and debt-collection requirements vary by provider type, payer, state and individual account.


Filed Under: Medical

Urgent Care vs Hospitals: Difference with Examples

Urgent Care Clinics Collection agency

Difference between Urgent care, ER, and Hospitals

  1. Urgent Care:
    • Purpose: Designed for urgent but non-life-threatening medical issues. Ideal for when you can’t wait for a regular doctor’s appointment but don’t need emergency room services.
    • Conditions Treated: Minor injuries like sprains, cuts that may need stitches, mild to moderate flu symptoms, minor infections, etc.
    • Hours: Often extended hours, including evenings and weekends, but not usually open 24/7.
    • Cost: Typically lower than ER visits.
  2. Emergency Room (ER):
    • Purpose: Equipped to handle severe and life-threatening conditions. They are open 24/7 and can provide immediate medical attention.
    • Conditions Treated: Heart attacks, strokes, severe bleeding, head trauma, serious injuries, severe breathing difficulties, etc.
    • Hours: Always open, 24 hours a day, 7 days a week.
    • Cost: Generally higher than urgent care, due to the resources needed for life-saving treatments and the variety of specialists available.
  3. Regular Hospital Visit:
    • Purpose: Scheduled visits for various medical needs that are not urgent or emergency. This includes regular check-ups, consultations with specialists, scheduled surgeries, and ongoing treatments.
    • Conditions Treated: Chronic conditions, follow-up visits, elective surgeries, specialist consultations, and more.
    • Hours: Typically during regular business hours, though hospitals themselves are open 24/7 for inpatient care.
    • Cost: Varies based on the services provided, but usually, it’s planned and often covered by health insurance.

Scenario-Based Examples:

  1. John’s Sports Injury: John injures his ankle while playing soccer. The pain is significant, but the ankle isn’t deformed, and he can bear some weight on it. He decides to visit an urgent care, where he is diagnosed with a sprain and given a brace and pain medication.
  2. Mary’s Chest Pain: Mary experiences sudden, severe chest pain and difficulty breathing. Her family calls an ambulance, and she is taken to the hospital’s ED. There, she is quickly evaluated for a heart attack.
  3. Regular Health Check-up: For his annual health check-up, Alex visits his local hospital, where his primary care physician conducts a thorough health examination and routine blood work.

Understanding Urgent Care Center Challenges

Urgent care centers face a unique set of challenges that differ from those encountered by regular hospitals. Here are some of the key challenges:

  1. Patient Volume and Flow Management: Urgent care centers often deal with unpredictable patient volumes, as patients walk in without appointments. This can lead to periods of overcrowding or underutilization, making staffing and resource management challenging.
    Example: An urgent care center may experience a sudden influx of patients during flu season, leading to longer wait times and a strain on available staff and resources.
  2. Limited Resources and Capabilities: Unlike hospitals, urgent care centers typically have fewer resources in terms of medical equipment and specialist availability. This limitation can affect the scope of treatments they can offer and may require referring patients to hospitals for more comprehensive care.
    Example: A patient with a complex fracture may visit an urgent care center, only to be referred to a hospital because the urgent care lacks the necessary orthopedic specialists and advanced imaging equipment.
  3. Staffing Challenges: Staffing in urgent care centers can be challenging due to fluctuating patient volumes. It’s difficult to predict when there will be a surge in patients, requiring a flexible and adaptable staffing model.
    Example: An urgent care center may find it challenging to maintain sufficient staffing on weekends or holidays, times when patient influx can be unpredictable but typically higher.
  4. Insurance and Billing Issues: Urgent care centers often face challenges with insurance reimbursements. They need to navigate a complex web of insurance plans, each with its own policies on coverage for urgent care services. This can lead to billing complications and difficulties for patients in understanding their financial responsibility.
    Example: A patient might visit urgent care for a minor procedure and later receive a bill that is not covered by their insurance, leading to confusion and dissatisfaction.
  5. Scope of Service Limitations: Urgent care centers are designed to handle non-life-threatening conditions, which can sometimes lead to misunderstandings among patients about the scope of services offered. Managing patient expectations about the type of care they can receive is a continual challenge.
    Example: A patient visits an urgent care center expecting comprehensive cardiac evaluation, but the center is only equipped to provide basic EKGs and must refer the patient to a hospital for more in-depth testing.
  6. Continuity of Care: Ensuring continuity of care is a significant challenge for urgent care centers, especially in communicating with a patient’s regular healthcare providers. Sharing patient records and ensuring follow-up care is coordinated effectively can be difficult.
    Example: A patient treated at urgent care for a minor injury may not have their visit details promptly communicated to their primary care physician, leading to a gap in their medical record.
  7. Regulatory Compliance: Urgent care centers must adhere to various health regulations and standards, which can be challenging given their limited resources compared to full-scale hospitals.
    Example: An urgent care center may struggle to keep up with the latest healthcare regulations, such as those related to patient data privacy or infection control, which are more easily managed in a hospital setting with dedicated compliance teams.
  8. Competition and Market Pressure: There is increasing competition in the healthcare market, with more urgent care centers opening and hospitals expanding their own urgent care services. This competition can impact patient volumes and the financial viability of these centers.
    Example: A new hospital-affiliated urgent care center opens nearby, offering similar services. This competition might lead to a decrease in patient visits to the independently operated urgent care center.
  9. Quality of Care and Patient Satisfaction: Maintaining high-quality care and ensuring patient satisfaction in a fast-paced, high-turnover environment is challenging. Urgent care centers must balance quick service with attentive and thorough medical care.
    Example: Due to the high turnover of patients, an urgent care center might receive feedback about rushed consultations, which could affect patient satisfaction and the perceived quality of care.
  10. Technological Integration: Implementing and maintaining up-to-date medical technology and electronic health records systems can be a significant investment and operational challenge, especially for independently operated urgent care centers.
    Example: An urgent care center might struggle to fund and implement a state-of-the-art electronic health record system, which is essential for efficient operation and is standard in most hospitals.

These challenges require urgent care centers to be highly adaptable, efficient, and patient-focused to provide effective and timely care while maintaining financial stability and regulatory compliance.

Filed Under: Medical

Medical Collection Agency for Doctors | 4.8-Star Rated & HIPAA Compliant

Unpaid patient balances shouldn’t linger in accounts receivable until they turn into bad debt. Once insurance pays its portion and internal billing stalls, a dedicated medical collection agency steps in so your staff can focus on patient care.

Collect911 recovers past-due medical and dental balances while protecting your practice’s reputation:

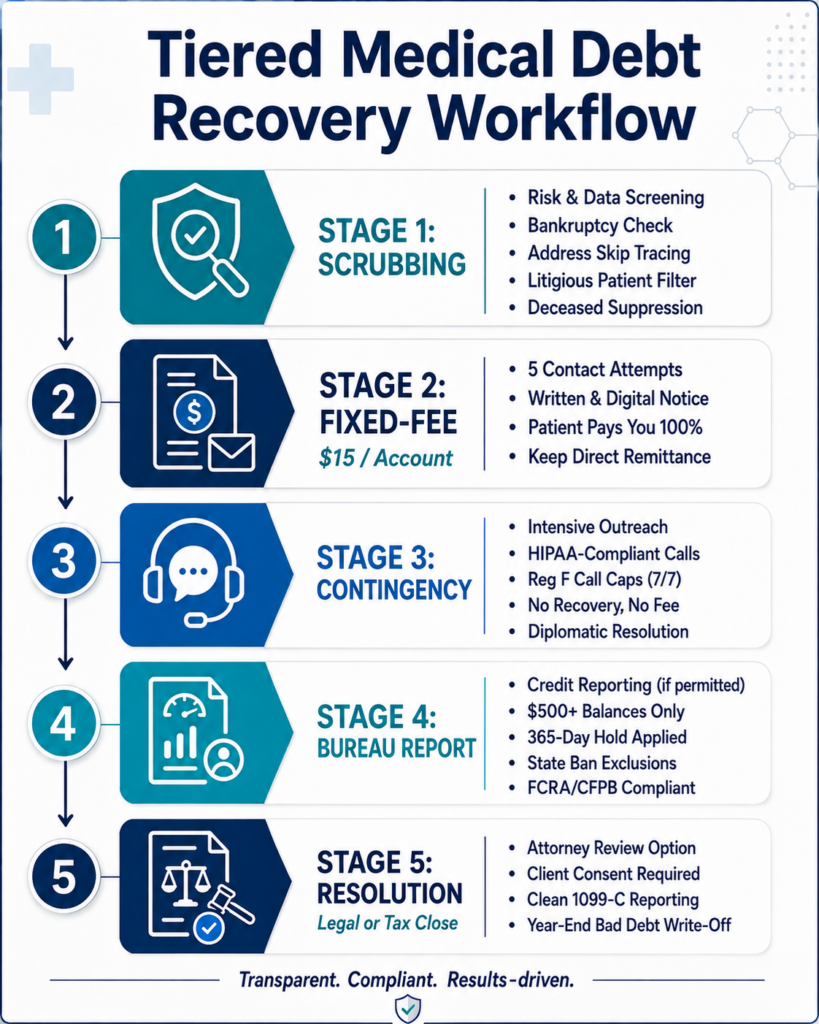
  • Fixed-Fee Recovery ($15/account): Ideal for newer balances under 90 days. Professional demand letters direct patients to pay you directly—your practice keeps 100% of recovered funds.

  • Contingency Collections: Performance-based recovery for older, unresponsive accounts. No recovery, no fee.

  • HIPAA-Compliant & Diplomatic: Secure, relationship-preserving outreach that resolves balances without aggressive tactics or negative patient reviews.

Diplomatic communication consistently outperforms high-pressure collection tactics—recovering revenue while keeping patients in your practice.

medical collection agency for doctors, highly rated and compliant


Protecting your practice’s reputation, Collect911 holds licenses in all 50 states, ensuring a safe approach for every patient interaction. We provide free litigation and bankruptcy scrubs with zero onboarding or annual fees. Our SOC 2 Type II and HIPAA-compliant systems ensure total data security, backed by a 4.85/5 rating from over 2,000 professional reviews. Delivering high recovery rates!

Need a Medical Collection Agency? Contact us


Tiered Medical Debt Recovery Workflow

Tiered Medical Debt Recovery Workflow


Our Strategy for Debt Collection

Patients fear collection agencies—and for good reason. Most expect aggressive calls, threats to their credit, and lawsuits.

We take the opposite approach: dignity, respect, and clear options.

Forceful tactics do not work. Respectful communication does. That approach protects your practice’s reputation, reflected in our 4.85-star Google rating—with 90% of reviews written by the patients we collected from.

Three realities every practice faces with aging receivables:

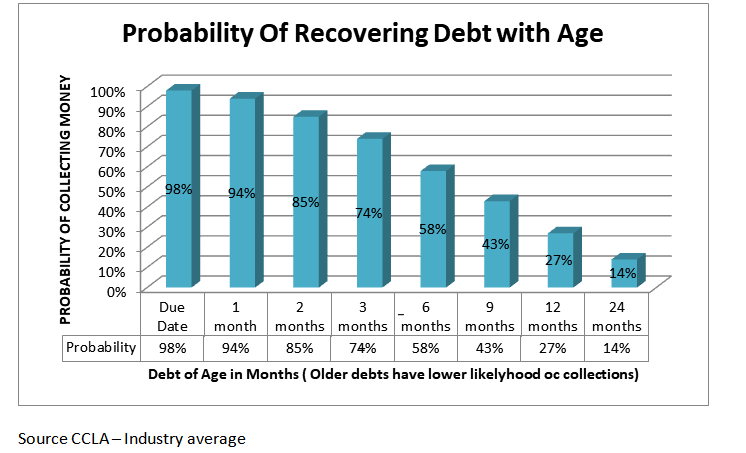
  • The 90-Day Cliff: After three billing cycles of non-payment, the chance of recovering that balance drops to near zero.

  • Staff Burnout: Your team hates chasing overdue balances, and doing it without dedicated training leads to costly errors. Letting unpaid accounts sit means writing them off as a 100% loss.

  • Compliance Landmines: Strict federal (FDCPA, HIPAA, Regulation F) and state laws govern medical collections. Collecting without expertise exposes your practice to expensive legal liability.

A professional agency turns write-offs into recovered revenue—without alienating your patients.

HIPAA and Data Security 

As part of these federal mandates, debt collection agencies must keep debtors’ information private and secure. Data provided by doctors and hospitals can have personal information, including SSN, DOB, and other sensitive information. All “Personally Identifiable Information” must be protected from fraud, theft, and any other means of being public.

A reputable medical debt agency will know that they must sign a “HIPAA Business Associate Agreement” to agree that they will comply with HIPAA regulations. 

Dealing with Insurance Companies 

Medical debt collection agencies are not just about going after unpaid patient debt. Doctors often have a nightmare dealing with insurance companies and getting the claim processed in a timely manner.

Insurance companies are legally liable to respond within a few weeks after receiving a collection letter. A collection agency will not generally make phone calls to an insurance company.

Using the same skills they use to settle debts with patients amicably and professionally, these companies can assist doctors and back-end personnel with insurance follow-up.

Experienced medical debt collection agencies have even been known to expedite insurance claims than usual.

Medical Debt Recovery Chances

Frequently Asked Questions:

When should a doctor’s office send an unpaid patient balance to collections?

A physician practice should first make sure insurance has processed the claim, contractual adjustments have been posted, and the remaining amount is truly the patient’s responsibility. After statements and reasonable internal follow-up have failed, continuing to let the balance age can consume staff time without improving cash flow. Newer delinquent accounts may be suitable for Collect911’s $15 fixed-fee program, while older or difficult accounts can be moved to contingency collections.

Should an insurance-denied medical claim be sent to patient collections?

Not automatically. Before treating a denied claim as patient debt, the practice should review the insurer’s Explanation of Benefits or remittance information, determine why the claim was denied, and establish whether the balance is actually the patient’s responsibility. Coding errors, eligibility issues, prior authorization problems, or appealable insurance denials may need to be resolved with the payer first. Only a properly established patient-responsibility balance should move through the patient collection process.

Can a doctor send a patient’s medical bill to a collection agency without violating HIPAA?

Yes. HIPAA permits healthcare providers to use collection agencies for payment activities. When the collection company functions as the provider’s business associate, appropriate HIPAA requirements apply, including a Business Associate Agreement and safeguards for protected health information. Information shared for collection purposes should also be limited to what is reasonably necessary to perform the collection activity.

What patient information can a doctor’s office give to a medical collection agency?

A physician practice may provide information reasonably necessary to identify the patient, establish the balance, and pursue payment, subject to HIPAA’s applicable requirements. Practices should avoid transferring unnecessary clinical information simply because it exists in the medical record. A HIPAA-compliant collection workflow should follow the minimum-necessary standard and appropriate data-security safeguards.

Can a doctor send a disputed medical bill to collections while a No Surprises Act dispute is pending?

For a bill that qualifies for the federal Patient-Provider Dispute Resolution process, the provider cannot move the disputed bill into collections or threaten collection while that dispute is pending. If the account was already in collections when the dispute began, collection activity on that bill must stop until the dispute is resolved. Practices should therefore identify qualifying billing disputes before escalating an account to collections.

Can a medical collection agency contact a spouse, parent, or guarantor about a doctor’s bill?

In certain circumstances, yes. HIPAA permits a healthcare provider or its collection agency to communicate with another person when reasonably necessary to obtain payment for healthcare services. However, disclosures must still comply with applicable privacy requirements, including limiting protected health information to what is reasonably necessary and honoring applicable confidential-communication restrictions. The responsible party or guarantor information in the practice’s records should therefore be accurate before an account is submitted.


Simple Pricing for Medical Collections

  • Fixed fee service – $15 per accunt
  • Contingency fee service – 40% of amount collected.
  • No hidden or onboarding fee.

Cost of collections. Contingency and fixed fee services.

Recent Recovery Results for Physician Practices:

Primary Care Practice — Fixed Fee — 72% Recovered

A multi-provider primary care practice placed $14,850 in unpaid patient-responsibility balances after insurance had processed the claims and routine billing follow-up was complete.

The newer accounts were submitted through Collect911’s $15 fixed-fee program.

Recovered: $10,692 — 72% recovery rate

The physician practice retained 100% of payments made directly to the practice.

Orthopedic Practice — Fixed Fee + Contingency — 61% Recovered

An orthopedic group submitted $32,700 in patient accounts, including deductibles, coinsurance balances, and older accounts that had stopped responding to internal statements.

Newer accounts entered the fixed-fee program, while older and more difficult balances were escalated to contingency collections.

Recovered: $19,947 — 61% recovery rate

Using two recovery stages allowed the practice to keep costs low on fresher accounts while applying more intensive recovery efforts to aging balances.

Specialty Physician Group — Contingency — 47% Recovered

A specialty medical group placed $41,500 in older patient balances after its billing staff had exhausted normal follow-up efforts.

The accounts were submitted to Collect911’s contingency collection program, with no collection fee on amounts that were not recovered.

Recovered: $19,505 — 47% recovery rate

Even though these balances were significantly aged, nearly half of the referred receivables were successfully recovered.


Need an experienced medical collection agency?

Contact us

Filed Under: Medical

Why the Best Medical Collection Agency Isn’t “Nearby”

Stop looking at the map and start looking at the metrics. What you need is results, compliance, and competence. Hiring a medical debt collector is a strategic partnership, not a local trade job like hiring a plumber or a carpenter.

Medical Collection Agency near me

When you search for a “medical collection agency near me,” you are looking for accountability, trust, and a partner who understands your local needs. But in today’s complex regulatory landscape, limiting your recovery options to your zip code is a dangerous gamble.

The most effective collection agency isn’t the one down the street—it’s the one with the best recovery rates, the strongest compliance infrastructure, and the ability to protect your practice from federal lawsuits.

The “Local Trap”: Why Proximity Doesn’t Equal Protection

Many medical practices hire a local agency thinking it will be easier to manage. But does that local agency truly understand the federal laws targeting healthcare collections today?

1. Do They Even Know What the “No Surprises Act” Is?

Healthcare billing has changed. The No Surprises Act protects patients from unexpected bills, and it has massive implications for how debts are disputed and collected.

  • The Risk: A generalist local agency that collects for gyms and mechanics may not understand the nuances of these medical-specific laws. If they misstep, your practice is the one on the hook for federal penalties.

  • The Solution: You need a partner who eats, sleeps, and breathes medical revenue cycle management. We stay ahead of every regulatory change so you don’t have to.

2. The GLBA & Data Security Reality

Most practices ask about HIPAA, but few ask about the Gramm-Leach-Bliley Act (GLBA). Federal law now requires non-banking financial institutions—including collection agencies—to have rigorous safeguards for customer data.

  • The “Low Fee” Warning: If you hire an agency just because they have the lowest fee, ask yourself: Where are they cutting corners? Often, it’s in data security.

  • The Hard Truth: Few local agencies can give you in writing that they are fully GLBA compliant. If they are running on outdated software to save money, they are exposing your patients’ data to hackers and your practice to potential lawsuits.


What Matters More Than Location?

Instead of asking “Are you nearby?”, top-performing medical practice managers ask these three questions:

1. Are You Secure & Compliant? (Get it in Writing)

Data security has no borders. We utilize state-of-the-art encryption and SOC 2 Type II compliant servers to protect your Protected Health Information (PHI). We don’t just “say” we are compliant; we prove it.

2. Do You Know the New Credit Reporting Rules?

The rules for reporting medical debt to credit bureaus (Equifax, Experian, TransUnion) have changed drastically. There are now waiting periods (365 days) and requirements to remove paid debts immediately.

  • A local agency using old habits can get you sued for Fair Credit Reporting Act (FCRA) violations.

  • We utilize automated systems that ensure every account is reported—or not reported—exactly according to the latest federal statutes.

3. How Do You Protect Our Reputation?

Your relationship with your community is your most valuable asset. We offer a diplomatic approach designed to protect your reputation during the process. Our collectors are trained in medical compassion, acting as an extension of your billing office to resolve balances without burning bridges.


Flexible Pricing for Every Practice

We don’t believe in “one size fits all.” We offer:

  • Contingency Fee Services: No recovery, no fee. Perfect for aging bad debt.

  • Fixed-Fee Services: Low-cost, flat-rate letters to resolve accounts early (often for less than the cost of a stamp and staff time).

By The Numbers: Why Trust Us?

  • 50-State Coverage: We are licensed/bonded to collect nationwide, solving the problem of patients moving out of state.

  • 24/7 Portal: You don’t need to drive to our office to see what’s happening. Our secure client portal gives you real-time access to reports, notes, and payments from your desktop.

  • Zero “Surprises”: Strict adherence to FDCPA, HIPAA, GLBA, and TCPA regulations ensures you are safe from liability.

Don’t Limit Your Recovery to Your City Limits

You shouldn’t have to choose between a “neighbor” and an “expert.” You deserve both: the personal service of a partner and the power of a national compliance powerhouse.

Collect911 connects you with top-tier medical debt specialists who understand the unique laws of your state—and the federal laws that supersede them.

Ready to boost your revenue securely? Stop looking for “nearby” and start looking for “paid.” Contact us today for a free analysis of your accounts receivable.

Looking for a good medical collection agency? Contact us

Filed Under: Medical

Dental Malpractice Insurance: A Guide for Private Practice

Protecting your license and your livelihood in a litigious era.

For dentists and oral surgeons, malpractice insurance is more than just a regulatory requirement—it is the firewall between a career-ending lawsuit and a minor administrative headache. However, not all policies are created equal. A “cheap” policy can leave you exposed to six-figure settlements that tarnish your National Practitioner Data Bank (NPDB) record.

This guide breaks down exactly what dentists need to know about coverage types, hidden clauses, and cost expectations for 2025.


1. The Two Main Policy Types

Most carriers (like MedPro, The Doctors Company, or Fortress) offer two primary structures. Choosing the wrong one can cost you thousands in “Tail Coverage” later.

Occurrence Policies (The “Gold Standard”)

  • How it works: Covers any incident that happens during the policy year, regardless of when the claim is eventually filed—even if it is 5 years later and you have retired.

  • Pros: No need to buy “Tail Coverage” when you retire or switch jobs. Simpler to manage.

  • Cons: Higher upfront annual premium.

Claims-Made Policies (The “Step Rate” Model)

  • How it works: Only covers claims filed while the policy is active. If you cancel the policy and a patient sues you a month later for an old root canal, you are not covered unless you bought an extension.

  • Pros: Much cheaper in the first 4 years (often starting at $500–$1,000/year).

  • Cons: You must purchase “Tail Coverage“ (Extended Reporting Endorsement) if you leave. Tail coverage typically costs 200% of your final year’s premium in one lump sum.


2. The “Consent to Settle” Clause (Critical for Dentists)

This is the single most important feature to look for in your policy.

The Scenario: A patient sues you for a “failed implant” that was actually caused by their own poor hygiene. You want to fight it to protect your reputation. Your insurance company wants to settle for $30,000 because it’s cheaper than going to court.

  • If you have “Pure Consent to Settle”: The insurer cannot settle without your written permission. You control your reputation.

  • If you have a “Hammer Clause”: The insurer can force you to settle. If you refuse, you may be personally liable for any judgment amount over the proposed settlement figure.

Trust Tip: Never sign a policy that doesn’t give you the right to refuse a settlement. A settlement shows up on your NPDB record forever.


3. What Does Malpractice Insurance Cost in 2026?

Premiums vary heavily by state (tort reform laws) and procedures performed (conscious sedation vs. general dentistry).

Estimated Annual Premiums (National Averages):

  • General Dentist: $2,200 – $4,500 per year.

  • Oral Surgeon: $12,000 – $45,000+ per year.

  • Recent Graduates: Often qualify for 50-75% discounts in their first year.

Note: States like New York and California often have premiums 30-50% higher than national averages due to higher litigation risks.


4. Common Dental Malpractice Claims

According to recent industry data, these are the top triggers for lawsuits against dentists:

  1. Extractions: Nerve damage (paresthesia) or jaw fractures.

  2. Endodontics: Instruments left in canals, perforations, or failure to diagnose infections.

  3. Implants: Placement failure or nerve impingement.

  4. Failure to Diagnose: Specifically Oral Cancer or Periodontal Disease.


Risk Management: The Connection Between Billing & Lawsuits

While insurance protects you after a lawsuit, your office protocols protect you before one happens. Interestingly, the same documentation that wins malpractice suits also secures your revenue.

The “Documentation Defense“ A detailed clinical note doesn’t just prove you met the Standard of Care; it also proves the service was rendered if a patient disputes the bill later.

  • Informed Consent: Must be specific to the procedure (e.g., “Risks of nerve damage discussed”).

  • Financial Consent: Clear, signed financial policies prevent patients from claiming “I didn’t know I had to pay.”


Here are 4 tips for dentists to find a great deal on malpractice insurance:

  • Compare Multiple Carriers: Don’t settle for the first quote; obtain proposals from at least three different A-rated carriers. Be sure to compare similar policy types (Occurrence vs. Claims-Made) to get a true apples-to-apples cost comparison.

  • Maximize Available Discounts: Actively ask about discounts for being a new graduate, working part-time, or completing risk management and patient safety seminars. These can significantly reduce premiums, especially in the early years of practice.

  • Calculate the Long-Term Cost of “Tail Coverage”: Before choosing a cheaper Claims-Made policy, estimate the future cost of the required “Tail Coverage” (often 200% of one year’s premium) upon retirement. An Occurrence policy, while more expensive upfront, may be cheaper over a full career.

  • Prioritize the “Consent to Settle” Clause: Do not choose a policy based on premium alone if it contains a “Hammer Clause” that lets the insurer force a settlement. A slightly more expensive policy with a “Pure Consent” clause gives you control over your professional reputation.

Frequently Asked Questions:

Does a dentist need tail coverage after leaving a practice or changing malpractice insurers?

If a dentist has a claims-made malpractice policy, tail coverage may be necessary when the policy ends, including when the dentist leaves a group practice, changes insurers, relocates, retires, or switches to occurrence coverage. Tail coverage, also called an Extended Reporting Endorsement, allows future claims to be reported for treatment provided while the original claims-made policy was active. Dentists should also check their employment agreement carefully to determine whether the dentist or the practice is responsible for purchasing and paying for tail coverage.

What is the difference between claims-made and occurrence malpractice insurance for dentists?

Occurrence coverage generally responds based on when the dental treatment or alleged incident occurred. If the treatment took place while the occurrence policy was active, a later claim may still be covered even after that policy has ended. Claims-made coverage generally requires the policy to be active when the claim is made and the treatment to fall after the policy’s retroactive date. Because of this difference, claims-made policies may require tail or prior-acts coverage when a dentist changes or terminates coverage.

What is a consent-to-settle clause in dental malpractice insurance?

A consent-to-settle provision determines how much control a dentist has when an insurance company wants to settle a malpractice claim. A pure consent-to-settle clause generally requires the dentist’s approval before the insurer can settle. A policy containing a “hammer clause” may create financial consequences if the dentist refuses a settlement recommended by the insurer and the eventual judgment or settlement is higher. Dentists should review the exact consent language rather than assuming all consent-to-settle provisions provide the same protection.

Does every dental malpractice settlement get reported to the National Practitioner Data Bank?

No. Whether a payment is reportable to the National Practitioner Data Bank depends on how the claim and payment are structured. Generally, an entity such as a malpractice insurer that makes a payment for the benefit of an identified healthcare practitioner in response to a written malpractice claim or judgment must report the payment to the NPDB. A payment made solely on behalf of a group practice or other multi-practitioner corporate entity may be treated differently when no individual practitioner is identified. There is no minimum dollar amount that automatically exempts an otherwise reportable malpractice payment.

Can refunding or waiving a patient’s dental bill trigger an NPDB malpractice report?

It depends on how the resolution is handled. Simply waiving a patient’s outstanding debt, with no money exchanged, is not considered a malpractice payment for NPDB reporting purposes. However, if an entity issues a monetary refund in response to a written malpractice-related demand involving an identified practitioner, the payment may be reportable. A dentist considering a refund or settlement after a patient complaint should therefore understand the insurance and NPDB implications before finalizing the arrangement.

What happens to malpractice coverage for treatment performed before switching insurance companies?

The answer depends largely on whether the dentist has occurrence or claims-made coverage. An occurrence policy generally continues to cover qualifying incidents that happened while that policy was active. With claims-made coverage, a dentist changing insurers should determine whether the new policy includes prior-acts or “nose” coverage, or whether tail coverage should be purchased from the previous carrier. The retroactive date is especially important because treatment performed before that date generally will not be covered by the new claims-made policy.

About Collect911

We are not an insurance carrier, but we are a partner in your practice’s financial health. We specialize in Medical & Dental Debt Recovery, helping practices across the USA recover the revenue needed to pay their overhead—including those rising malpractice premiums.

Our philosophy is “Diplomacy First.” We understand that a gentle, respectful collection process reduces the risk of patient retaliation, keeping your practice safe and solvent.

Contact us for a free practice financial analysis

Filed Under: Medical

Looking for a Medical Collection agency Near You?

Medical Collection Agency near me
Having a Medical Collection Agency near you has no advantages.

A debt collector does not personally go to collect money from your patients, therefore it is immaterial if a patient receives Collection Calls or Letters that have originated from your own city or somewhere from California or New Jersey.

In-fact if you are limiting your search of a Collection Agency located near you, most likely you are missing out on hiring a Collection Agency that could have recovered a lot more money from your patients.

When you need to hire a plumber or a cleaner you go local, but do you know from which city do your monthly Electric or Phone statements are generated. Do you know from which city of America do you get a phone call regarding your Bank Account or regarding your upcoming Flight Status. Do you even care? Debt collection is one of the activity where physical location of the agency really does not matter. 

Medical Collections is very tricky, the agency handling your accounts receivable should clearly understand the delicate nature of doctor-patient relationship. Collections should be made in a diplomatic, systematic and amicable manner, in an attempt to preserve the doctor-patient relationship.

Important requirement – Your medical collection agency should be licenced to collect in your state, and apart from English speaking collectors, they should have Spanish speaking debt collectors as well.

If all direct collection efforts fail and a lawsuit is advisable, then nearly all Collection Agencies have a nationwide network of experienced lawyers in pretty much every city of America. It is a part of their standard collections process. Contingency fees is disclosed in advance depending on the complexity of the case.

All medical collection agencies are required to follow all federal and state laws like the Fair Debt Collection Practices Act (FDCPA), Fair Credit Reporting Act (FCRA), Telephone Consumer Protection Act (TCPA) and Health Insurance Portability and Accountability Act (HIPAA) guidelines.

Apart from a higher recovery rate, ask if the collection agency has an online portal where you could submit new accounts, run reports and stop the recovery process of an account where a payment has been received. Are their call centers located in USA or in a foreign country. What all steps do they take to protect the personal data of your patients and if they have any 3rd party security certificates to prove that.

Bottom-line, if you are looking for a “Medical Collection Agency near me“, you will likely miss hiring the best debt collection agency in medical field. 

In Medical Collections, demand letters sent by a Collection Agency are extremely effective and a low cost solution. Ask your collection agency if they offer Collection Letters service or not, they cost roughly $15 an account. Best suited for accounts less than 120 days past due.

Medical collections are relatively more prone to legal action from aggravated patients. To protect your medical practice from running into these lawsuits, your Collection should perform Litigious Patient check. It means if the patient has a history of suing Small Businesses or Medical Practices then the agency should appropriately advice you. Moreover, the agency should be fully insured to protect them-self and your practice in case a lawsuit is filed by a patient.

It is advisable to transfer an account to collections if a patient has not cleared their medical bill within 60 to 90 days and your own staff has not been successful to recover money during this time-frame.

Looking for a medical collection agency? Contact us.

Filed Under: Medical

  • Page 1
  • Page 2
  • Go to Next Page »

Primary Sidebar

Highly Rated Collection agency: 4.85-Star Rating / 2,200+ Reviews
Contact Us:

Need a Collection Agency?
Kindly fill this form.
We’ll get in touch with you


    Please prove you are human by selecting the cup.

    • Free Bankruptcy screening.
    • Free Credit Reporting (If law permits).
    • Free Change of Address check
    • Litigious defaulter check.
    • A 5-star rated agency !

    Our aim is to provide all debtors a convenient path towards eliminating their debt in a consumer friendly manner.

    Featured Posts

    • Dentrix Dental Collection Agency: The Ledger-Safe Solution: HIPAA Compliant
    • Credit Unions: Turn Overdue Accounts Into Recovered Revenue
    • Funeral Homes Unpaid Invoices: Hire a Collection Agency
    • Restoring Texas Medical Vitality: Medical Collection Agency
    • Florida’s Healthcare Debt Specialists: Recovering Revenue in the Sunshine State

    Exclusive Posts

    • Responsibility-to-Notification Days: The Patient Billing Delay Your A/R Report Doesn’t Show
    • Top Hospital & Medical Collection Agency in Indiana
    • Top Nevada Collection Agency for Patient Revenue Cycles
    • Idaho Medical Collection Agency: Recover Patient Balances
    • Georgia Medical Collection Agency: Recover Patient Balances
    • Delaware Medical Collection Agency: Recover Patient Balances
    • Colorado Collection Agency: Modern Revenue Cycle Strategies
    • Top Arkansas Collection Agency for Patient Account Solutions
    • Top Arizona Collection Agency for Patient Account Solutions
    • Top Alaska Collection Agency for Patient Account Reconciliation
    • Top Alabama Collection Agency for Unpaid Patient Bills
    • Respectful Medical Collections for Ohio Clinics & Hospitals
    • Medical Collection Agency in Illinois: Recovering Patient Bills
    • Medical Collection Agency in Pennsylvania: Recovering Patient Bills
    • Restoring Texas Medical Vitality: Medical Collection Agency
    • Healthcare Collection Agency: Restoring California’s Medical Vitality
    • Best Collection Agency LA & San Diego: Medical & Business Recovery
    • The 90-Day Deadline: When to Stop Calling and Start Collecting
    • The Bursar’s Guide to Ethical Tuition Recovery | Surviving the Transcript Ban
    • Collection Agency Market Overview
    COPYRIGHT: COLLECT911 | 2026
    This content is provided for general informational purposes only and should not be considered legal advice. Collection laws and requirements may vary by state, account type, documentation, debtor status, and specific facts. Please consult qualified legal counsel for guidance regarding your particular situation. Collect911 and its authorized collection partners service accounts in accordance with applicable federal and state collection requirements. Visit our home page to know more about us.
    X
    Need a Collection Agency?
    Contact Us